

Information
This guideline is aimed at all clinical health care professionals and nursing staff in NHS Lothian. It is designed to provide safe, practical guidance in the screening, diagnosis and management of complications related to ADULTS on long term high dose steroid therapy initiated in primary or secondary care.
Abbreviations: PPI = proton pump inhibitor, BGM = blood glucose monitoring, CGM = continuous blood glucose monitoring (such as dexcom or libre devices), BG = blood glucose, SU = sulphonylurea.
LONG TERM HIGH DOSE STEROID THERAPY = ≥ 10mg prednisolone (or equivalent) for > 14 days
| Prednisolone 10mg approx equivalent to |
|---|
| Hydrocortisone 40mg |
| Dexamethasone 2mg |
| Methylprednisolone 8mg |
| Betamethasone 2mg |
THINGS TO DO AT COMMENCEMENT OF LONG TERM STEROID THERAPY
- PERFORM an HbA1c and warn patient of symptoms of hyperglycaemia
- Hyperglycaemia is a potentially severe side effect of long-term steroid therapy particularly in the elderly and those with pre-existing diabetes.
- See Hyperglycaemia screening and management in the context of long term steroid use – RefHelp page for further information.
- GIVE ADVICE ON ‘SICK DAY RULES‘ and give STEROID EMERGENCY CARD & LONG TERM STEROID USE PIL (see Resources and Links) – For advice on how to safely withdraw long term steroids, see Primary Care Management section.
- GASTROPROTECTION
- PPI therapy should not be given routinely but should be considered for people at high risk of gastrointestinal bleeding or dyspepsia. (e.g. previous GI bleed, known GORD/peptic ulcer disease, currently on anticoagulation or active cancer).
- BONE PROTECTION:
- On prednisolone 7.5mg daily for 1-3 months: prescribe calcium/vit D
- On prednisolone 7.5mg daily >3 months: Consider starting bisphosphonate treatment if the BMD T-score at any site is less than -1.5 (Treatment can be commenced while awaiting the results of DEXA) OR if they are aged 60 years and above. See Corticosteroid Induced Osteoporosis – RefHelp.
STEROID ‘SICK DAY RULES’ AND SAFE STEROID WITHDRAWAL
Definition of ‘at risk of adrenal crisis’:
Patients prescribed steroids at >5mg/day prednisolone (or equivalent) for over 4 weeks are at risk of adrenal suppression and therefore may be at risk of adrenal crisis.
| Steroid | Dose Equivalent |
|---|---|
| Prednisolone | 5mg per day or more |
| Methylprednisolone | 4mg per day or more |
| Hydrocortisone | 15mg per day or more |
| Dexamethasone | 500 microgram per day or more |
Patients at risk of adrenal crisis should be issued a STEROID EMERGENCY CARD (see Resources & Links) and can be found at www.endocrinology.org/adrenal-crisis)
Sick day rules
| Patient taking | <10mg prednisolone (or equivalent) | 10mg prednisolone or more (or equivalent) |
| Fever, infection needing antibiotics, surgery under local anaesthetic | Increase dose to 10mg prednisolone (or equivalent) whilst unwell or on day of procedure | Continue usual glucocorticoid dose |
| Persistent vomiting, preparation for colonoscopy, acute trauma, surgery under anaesthetic | 100mg Hydrocortisone IM/IV at onset/presentation/start of procedure then 50mg hydrocortisone IV QDS. Patient should be admitted for ongoing parenteral hydrocortisone if required. | 100mg Hydrocortisone IM/IV at onset/presentation/start of procedure then 50mg hydrocortisone IV QDS. Patient should be admitted for ongoing parenteral hydrocortisone if required. |
| Patients with confirmed adrenal insufficiency lasting >3 months should be seen in endocrine clinic for education about sick day rules and emergency hydrocortisone injection | ||
Sick day rule dosing for patients at risk of adrenal crisis (see above) is as follows:
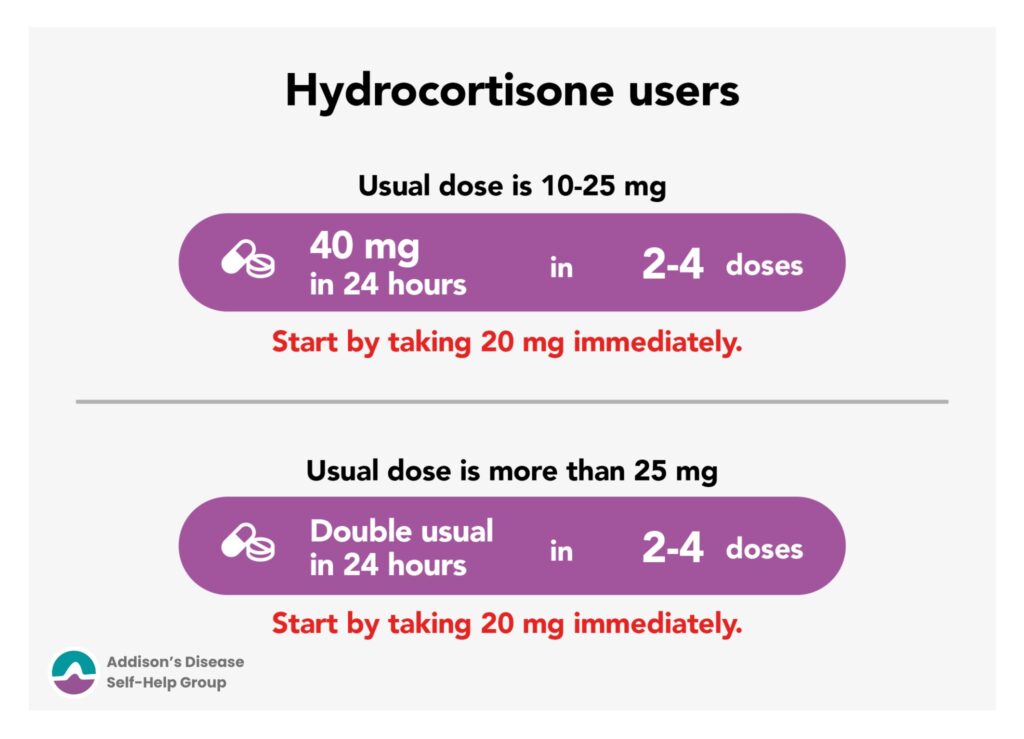

Images courtesy of www.addisonsdisease.org.uk
For Screening and management of Hyperglycaemia in the context of steroid use, see Hyperglycaemia screening and management in the context of long term steroid use – RefHelp
M.L, A.S, T.C. & M.A – 16-9-26
Please see Primary Care Management section for Steroid withdrawal guidance.
Who can refer
GPs, Secondary care clinicians
Who to refer
Patients who require Short Synacthen Test as per flowcharts in Primary Care Guidelines section
Who not to refer
Please follow flowcharts in Primary Care Guidelines
How to refer
For arranging SST use SCI gateway : WGH/RIE > Enocrinology > Basic Sign Referral
STEROID WITHDRAWAL ADVICE
Responsibility for safe weaning and withdrawal of steroids, including short synacthen test, resides with the secondary care service initiating the steroid treatment. If steroids were initiated in primary care and a short synacthen test is required, please refer to endocrinology.
Further guidance for steroid withdrawal can be found in the NICE guideline NG 243 “Adrenal insufficiency: identification and management” under the section “Managing glucocorticoid withdrawal to prevent adrenal insufficiency” Overview | Adrenal insufficiency: identification and management | Guidance | NICE. Testing for adrenal insufficiency should be considered only for patients with symptoms of adrenal insufficiency .
For ADULTS (>16 year) who have been taking glucocorticoids to treat an underlying condition 4-12 weeks, have not had repeated courses of steroid in the last year, and no longer need them:
- Stop the prescribed glucocorticoid
- Offer ‘Stopping your course of steroids’ PIL and
- Consider assessment of adrenal reserve if the patient develops symptoms of adrenal insufficiency (flowchart 1 below)
For people who have been taking glucocorticoids for more than 12 weeks and no longer need them
- reduce the prescribed glucocorticoid to a physiological equivalent dose (Hydrocortisone = 15mg, prednisolone = 3mg, dexamethasone = 0.5 mg) or consider a slow taper,
- Offer ‘Stopping your course of steroids’ PIL and
- After 6 weeks consider stopping the steroids or continuing with a slow taper
- If the patient develops symptoms during the slow taper or after stopping consider assessing adrenal reserve (Flow chart 1).
- If needed a very slow tapering plan can be found here Prednisolone withdrawal
| Symptoms of not producing enough steroid hormone |
|---|
| Symptoms of not producing enough steroid hormone |
| Feeling more tired, especially in the morning |
| Feeling lightheaded when you stand up, or fainting |
| Aching or stiff joints |
| Low mood |
| Struggling to finish things/ poor concentration |
| Feeling weak |
| Feeling nauseous |
If adrenal crisis is suspected in patients at risk, treatment is as follows:
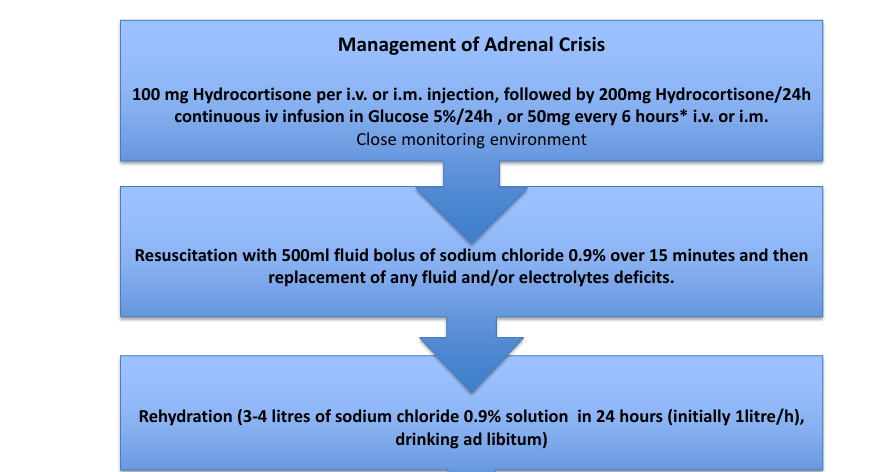
For perioperative and obstetric management please discuss with the anaesthetic team and consult national guidance (Management of glucocorticoids during the peri-operative period for patients with adrenal insufficiency | Association of Anaesthetists – www.anaesthetists.org)
Stopping your course of steroids PIL
Hyperglycaemia PIL – link to be updated
Gliclazide tablets for steroid induced diabetes
Society for Endocrinology free steroid emergency card and guidance Adrenal crisis | Society for Endocrinology














